
Safeguarding and gender service investigations

In August 2020, a doctor in Worthing raised concerns about a GP prescribing puberty blockers and cross-sex hormones. Six years later, an independent investigation found that the clinic the GP led had caused “actual potential harm” to children. The whistleblower who raised an alarm that wasn’t heeded is now in an employment tribunal against her former employer. Nick Wallis’s account draws from documents released for a tribunal which is currently in process: Redvers v NHS Sussex and Adam Doyle. Dr Redvers is making a case for constructive dismissal. NHS Sussex denies liability.

Prescribing beyond the scope

In 2020, concerns were raised about a young patient, who was anorexic, had mental health difficulties and had been prescribed testosterone by GenderGP, the online clinic founded in 2015 by Abergavenny GP Helen Webberley. In 2018 Dr Webberley was convicted of running an unregistered medical agency. She moved GenderGP abroad. It now operates from Singapore, referring patients, children included, to prescribers in the European Economic Area. At WellBN in Brighton, according to the New Statesman, children who had started on puberty blockers with private providers had their prescribing taken over by the practice.

These concerns reached Dr Sarah Redvers, the named GP for safeguarding in West Sussex. Dr Redvers informed her superiors of a “reasonable suspicion” that Dr Sam Hall, a GP, lacked training and “may be prescribing beyond…scope”. Her concerns were flagged to NHS Sussex and NHS England. However, a local review in May 2021 found “no causes for concern.”

Targeting the whistleblower

The review noted that one person’s “persistent interest in the issue appeared disproportionate”, an allegation which Dr Redvers inferred to be aimed at her. The General Medical Council closed its case against Dr Hall in July of the same year. Dr Hall then alleged that Dr Redvers and her safeguarding team were transphobic. Within weeks, the scrutiny flipped from Hall to Redvers. Redvers was not cleared so promptly. She describes a four-hour interview that had to be stopped because of her distress. A later grievance investigation found in her favour on 14 counts, and NHS Sussex apologised for their treatment of her. In a separate personal injury claim, NHS Sussex admitted liability. By then, she says, she had concluded that raising any further safeguarding concerns around WellBN would be catastrophic for her health and for her career.

On the record

None of this was secret. In August 2025, ten months before the investigation reported, Hannah Barnes revealed in the New Statesman that the 2020 concerns had led to an internal NHS England investigation. It found no professional concerns, pointed instead to long NHS waiting lists and appeared to imply that the complaint was motivated by transphobia. The General Medical Council received at least three complaints between 2021 and 2024, two of them from parents of 16-year-olds being prescribed hormones. One said that their child had forged their signature to get a first prescription. Each time, the General Medical Council found no case to answer. WellBN’s partners wrote to NHS Sussex in April 2025 that they had been starting treatment for 16-year-olds “with full transparency and with your express knowledge” for five years. Dr Hall told Trans Pride Brighton that summer: “I’ve been doing [it] for the last five years with the full knowledge of everybody in the system… What’s changed? Nothing.”

Actual harm

Dr Hall joined WellBN, a GP practice in Brighton, in 2019, and was one of its three partners by the time she left. In July 2022, the Care Quality Commission rated the practice “inadequate”. In 2024, following the Cass Review, puberty blockers were banned outside a research trial, and the review had urged “an extremely cautious clinical approach” to hormones before 18.

Ultimately, it was a legal challenge that grabbed the NHS’s attention. In 2024, the father of a child treated at WellBN applied for a judicial review. Dr Redvers claims that it was this that made NHS Sussex realise that it could be held to account for the shoddy practices in the clinic. Barnes’s reporting supports this. Less than two months after the General Medical Council closed its third complaint, NHS England told NHS Sussex that WellBN should stop prescribing hormones to 16- and 17-year-olds. NHS Sussex narrowed that to new patients only, so children already on hormones kept getting new prescriptions while the investigation was under way. “What had changed,” Barnes wrote, “is that the NHS was facing legal action.” This is a familiar pattern: despite several whistleblowers and wholesale resignations at the Tavistock, it was Keira Bell’s lawsuit that brought it under public scrutiny.

An independent patient safety investigation was agreed in May 2025. Dr Hall left WellBN that July. The investigation report, published in June 2026, found that WellBN had caused “actual potential harm” and “fell substantially below” required standards. Puberty blockers and hormones had been prescribed without a full assessment: in 22 cases without even a face-to-face appointment taking place. The investigation was restricted to the 78 patients who were still under 18 when it was commissioned. According to Dr Redvers, more than 2,000 others treated at WellBN fell outside its scope because they had turned 18 at the time of the investigation.

Parallels

Welsh Government and NHS Wales should be paying attention to the parallels.

Lack of scrutiny: At WellBN, concerns were raised by a GP in another town and an NHS safeguarding lead, not from the clinic’s own oversight. In Wales, NHS Wales ordered a review of the Welsh Gender Service in July 2024 after complaints, then took two years to start it. The surgical pause in August 2026 followed data showing that the service was referring patients for surgery at four times the English rate, concerns raised by clinicians in NHS England and sustained attention from Nick Wallis. The impetus to investigate, again, came from outside the service.

Internal culture: In both WellBN and the Welsh Gender Service, gender medicine was framed less as a clinical specialism and more of a moral cause: a “movement”, in the words of the Welsh Gender Service’s former clinical director, Dr Sophie Quinney. When questioning a treatment is treated as an attack on patients, and staff share a political commitment, few will risk raising concerns.

Advocate leadership: Dr Hall has written about a personal investment in gender medicine. Until recently, the Welsh Gender Service was led by Dr Quinney, who described herself in a 2020 video as part of the “movement to improve healthcare for trans and non-binary people” and as using “a gender-affirmative approach”. Nick Wallis noted her signature on an open letter expressing a “deep lack of confidence” in the Cass Review. A service led by individuals committed to an ideologically driven model of care will struggle to see its failures.

Who reviews the reviewers: Barnes noted that the Sussex investigation was led by the two bodies that had been warned for years and did nothing, and that its panel included two psychologists from NHS children’s gender services. Welsh Government has not yet said who the Welsh Gender Service reviewers are, or how independent they will be from the model of care under review.

Ministerial pressure for a ‘swift review’ should not cut the investigation short. Whatever data the Welsh Gender Service has not made public should be gathered and published – with such alarming headline figures, we need to know whether safeguarding and patient care have been compromised.
Review of the Welsh Gender Service

On 5 October, Cardiff and Vale University Health Board published the terms of reference for the independent clinical review of surgical referrals from the Welsh Gender Service. For most of this year, almost everything the public knew about the service came from one source: Nick Wallis’s reporting on the excellent GenderBlog. The terms of reference confirm most of what he reported, deal with several of his concerns, and leave some important questions unanswered.

How we got here

In May, Wallis used freedom of information data to show that the Welsh Gender Service was referring patients for surgery at three to four times the UK rate per head of population. Wales has under 5% of the UK population, but it accounted for 16% of all NHS referrals for masculinising chest surgery in 2025 and 20% in 2024. He also reported that the service could not say how many of its patients it recommended for cross-sex hormones, because that information was “not centrally recorded or collated” and that an independent review of the service, ordered by the NHS Wales Joint Commissioning Committee in July 2024, had still not begun.

In August, he found an internal paper describing the service as a “potential Service of Concern”. The same paper said the long-delayed review would focus on the non-surgical parts of the pathway, while surgery referrals carried on. Days later, the Joint Commissioning Committee paused all surgical referrals, assessments and scheduled operations. Its update of 3 September noted that a markedly lower proportion of Welsh patients were going on to have surgery than patients referred from English services, which raised questions about whether some had been properly assessed for basic requirements such as overall fitness for surgery.

By mid-September, a review panel had been appointed to look at around 60 patients by Christmas. The committee reported that clinicians in NHS England had raised concerns about the “appropriateness of referrals and clinical suitability”, which was echoed in complaints from the public. The separate, long-promised review of the whole service had finally started.

What the terms of reference confirm

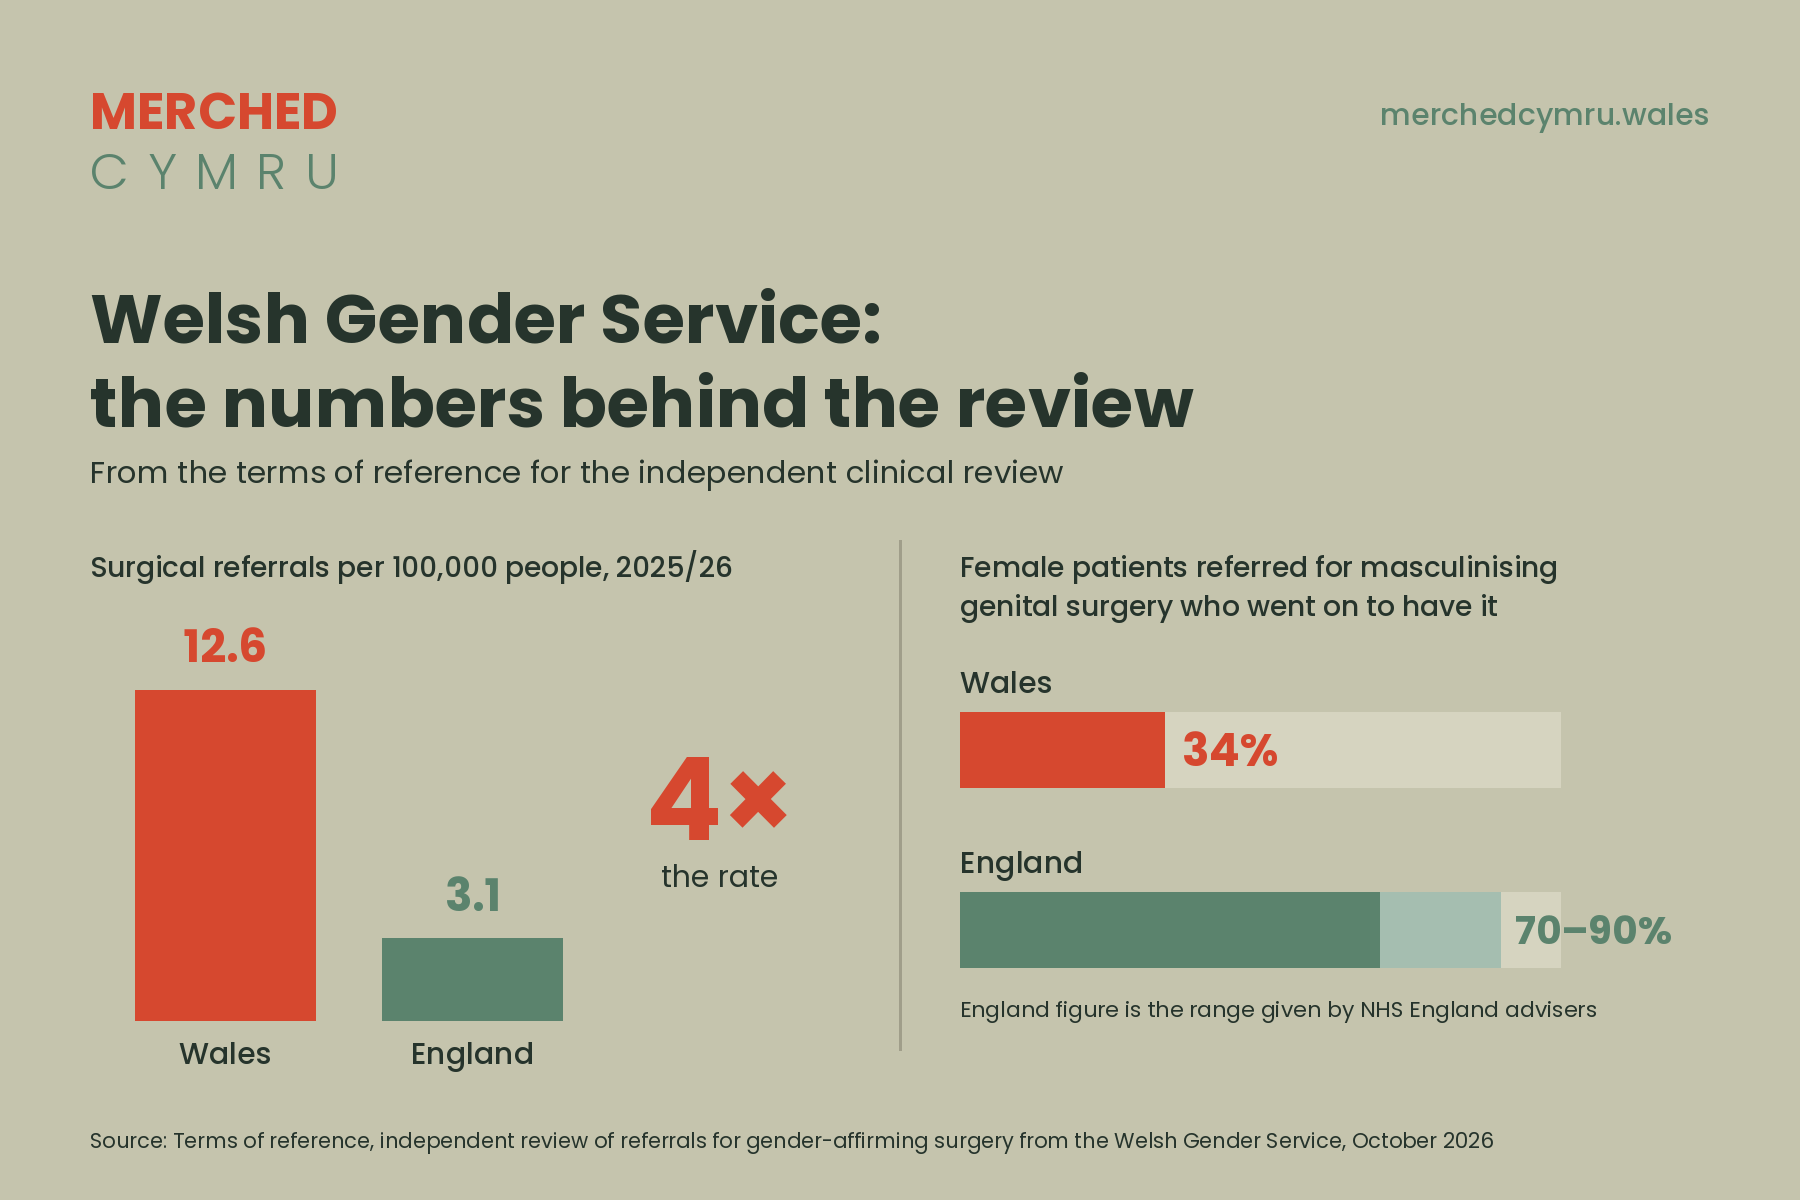
The terms of reference set out the case for the review more plainly than any official statement so far. In 2025/26, the Welsh Gender Service referred patients for surgery at 12.6 per 100,000 people, against 3.1 per 100,000 for gender services in England. That is four times higher overall, and three to five times higher depending on the procedure. The progression figure is starker still. Only 34% of female patients referred from Wales for masculinising genital surgery went on to have it, against roughly 70 to 90% for English services. The terms of reference cite “concerns expressed by clinical advisers and information arising through complaints”. They conclude that keeping the pause in place is “the safest option”.

In other words, the official account matches what Wallis reported week by week, often in the face of hostility and official silence.

Where the terms of reference meet the concerns

The terms of reference address several problems Wallis and others had raised.

Surgery is now under review. In August, the planned review was described as focusing on non-surgical aspects of the pathway. There is now a dedicated surgical review, and its findings must feed into the wider review of the service.

There is a clear standard. Each case will be judged against the NHS England service specification, using a framework agreed before any case is opened. The assessment covers mental health, physical health and, where clinically indicated, “relevant forensic or safeguarding history”. Reviewers must ask whether “wider health needs” were properly assessed – the concern raised in September.

The safeguards against a whitewash are written in. A patient being ready for surgery now does not, on its own, show that the original assessment was adequate. The absence of concerns in an initial convenience sample “should not alone be treated as assurance” about the wider service. If the first cases reviewed are not representative, more should be sampled. Urgent safety concerns are to be escalated immediately, without waiting for a report. No recommendation counts as complete until there is evidence that it has made a difference in practice.

This is a serious document, and it deserves credit for that.

The policy behind the practice

For several years, Welsh policy underpinned this pull towards medicalising issues around gender, as Ben Sears has documented in a series of pieces for Genspect.

In 2021, Welsh Government convened an Independent LGBTQ+ Expert Panel. Of its 13 members, two came from Stonewall, and one was the Welsh Gender Service’s own clinical director. The panel recommended an affirmative approach to care “in line with international clinical standards”, which its report tied to WPATH, the World Professional Association for Transgender Health. It also recommended a model led by primary care, in which GPs could start hormone treatment. It urged a “de-pathologised” approach, away from what it called the “traditional psychiatric approach” with its “intrusive and degrading questioning”. Many of these recommendations went into the Welsh Government’s 2023 LGBTQ+ Action Plan. The plan committed to cutting waiting times for the Welsh Gender Service and hormone prescriptions.

According to the “WPATH in the UK” report, drawn from the WPATH Files, the NHS Wales commissioning policy for adult non-surgical gender services referred to the WPATH Standards of Care. In May 2024, weeks after the Cass Review was published, then Health Minister, Eluned Morgan, told the Senedd that NHS Wales was working to align with its recommendations. That commitment concerned children’s services, though, and the Action Plan was never revised. In the 2026 election campaign, Plaid Cymru committed to continuing the plan and to protecting access to Welsh gender services.

A national policy that treated thorough psychological assessment as intrusive, shaped in part by the service’s own leadership, would make that medicalising gender distress more likely. The review measures the service against the NHS England specification, but Welsh policy has been asking it to work to a different standard. Whatever the reviewers find, their findings will reflect on Welsh Government’s choices as well as the WGS.

What the terms of reference don’t answer

Who are the reviewers? The document describes them only as “experienced independent gender clinicians”. Nothing is published about who they are, where they come from, or how independent they are of the practice under review. In September, Wallis pointed out that the health board had reaffirmed its commitment to “gender affirming care” before the review had even begun. Reviewers need to be independent.

Will it stop at 30? There is an interim review after 30 patients. If assurance is found at that point, the remaining stages may not go ahead. The criteria for that decision have to be agreed in advance, and the safeguards above are meant to stop a premature conclusion. But those criteria have not been published. We would like to see them.

What about hormones? Wallis reported that the service did not centrally record how many patients it recommended for cross-sex hormones. Health board figures he obtained put the monthly rate at between 51% and 88% of patients. The escalation applies only to surgical referrals. Psychological and endocrine services, including hormones, carry on as before. The surgical review will not examine them. Hormone treatments are often gateways to surgery, so any assessment problems earlier in the pathway fall to the wider service review. We need transparency to fully understand the processes.

Is the standard correct? The review asks whether referrals met the NHS England specification. It does not ask whether surgery was the right answer for these patients at all. The Cass Review found the evidence base for gender medicine weak. Some clinicians argue that a preferable goal is helping people come to terms with their sexed bodies rather than changing them. Measuring the Welsh Gender Service against the English standard is a reasonable place to start, but it does not address fundamental questions about these surgeries in the first place.

Will the reviewer be able to work without pressure? The First Minister has said he will be guided by the clinical evidence, but wants the matter resolved “quickly”. Ministers sought assurances that this was “a pause, not a stop”. Twenty-six of Plaid Cymru’s 28 backbench Members of the Senedd have written expressing “profound disappointment” at the pause, and an violent activist group has issued a warning to the commissioning committee: “Expect us.” The terms of reference ask the commissioners to confirm they have the resources to finish the job “without compromising the quality or consistency of the review”. The review needs to be conducted without activist or political pressure.

The test ahead

The original independent review was ordered in July 2024 and had not started two years later. In that time, hundreds of patients were referred for irreversible surgery. People who detransition face a heavy stigma, often including the loss of the communities that once supported them, and many never speak publicly. Wider coverage of this review may change that. If the review finds that patients were referred without proper assessment, some may decide to take legal action. Claims of that kind would be brought against Cardiff and Vale University Health Board, and larger settlements are met through the Welsh Risk Pool. In other words, they would be paid for by Welsh taxpayers. That would be the price of a Welsh Government that took two years to start a review it had ordered itself, and of a Welsh health board whose oversight missed problems that clinicians in NHS England flagged.

That is a potential cost to Wales. More serious is the potential for clinical harm to individuals who have passed through the doors of the Welsh Gender Service and may have been let down by a service whose approach put affirmation before assessment.